
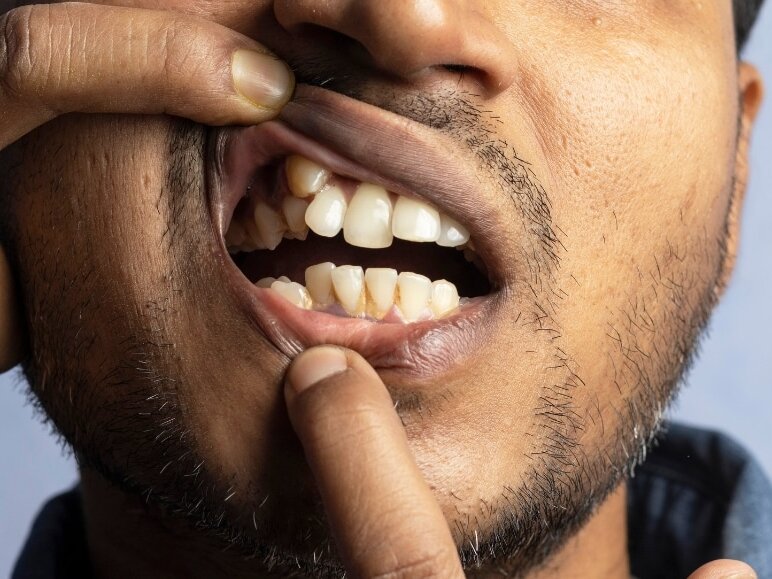
Hyperdontia describes the presence of extra teeth beyond the standard set of 20 primary or 32 permanent teeth. The condition reaches far past a simple counting problem, touching eruption patterns, bite stability, and the long-term health of neighbouring teeth. This guide covers hyperdontia causes, the signs that surface in daily life, how dentists confirm the finding, and which hyperdontia treatment paths suit different cases.
What Is Hyperdontia?
Hyperdontia is the clinical term for supernumerary teeth, meaning any tooth that develops in excess of the normal dental formula. Children typically carry 20 primary teeth and adults 32 permanent teeth, so a child with 21 teeth or an adult with 33 already meets the definition. The extra tooth may sit neatly in the arch, crowd its neighbours, or stay buried in bone for decades without announcing itself.
The condition appears in both dentitions, which is why hyperdontia supernumerary teeth turn up in paediatric charts and adult records alike. According to a review published in the Journal of Clinical and Experimental Dentistry, prevalence runs between 0.3% and 0.8% in primary dentition and between 1.5% and 3.5% in permanent dentition. Males are affected more frequently than females, a pattern consistent across population studies.
One Extra Tooth or Several
Most people with hyperdontia carry a single supernumerary tooth. Cases involving more than two extra teeth account for fewer than 1% of all presentations, and that cluster pattern raises the likelihood of an underlying syndrome. The teeth may appear on one side of the mouth or both, in the upper jaw, the lower jaw, or across both arches, and they can emerge alone or in small groups.
Signs of Hyperdontia and Extra Teeth Growing in Gums
The clearest indicator of hyperdontia is a tooth appearing where no tooth belongs, whether in front of, behind, or beside the existing row. Many patients first notice teeth growing in gums at an odd angle, or a child’s permanent tooth taking far longer to arrive than its counterpart on the opposite side. Discomfort is not a reliable marker, since a buried supernumerary tooth often produces no sensation whatsoever.
Several patterns tend to surface before a diagnosis is made:
- A visible extra tooth erupting behind or between the front teeth
- A growing tooth in gum tissue that sits outside the normal dental arch
- Delayed eruption of a permanent tooth while its pair has already come through
- A primary tooth that refuses to loosen long past the expected age
- Crowding, rotation or a midline gap between the upper central incisors
- Pressure, swelling or tenderness in the gum during chewing
- Difficulty cleaning between teeth that sit unusually close together
Single symptoms rarely confirm anything on their own. A combination of delayed eruption and localised crowding, however, gives a dentist strong reason to investigate further with imaging.
Hyperdontia Causes and Associated Conditions
The precise mechanism behind hyperdontia remains unsettled. The leading explanation points to hyperactivity of the dental lamina, the band of tissue from which tooth buds form, producing an additional bud alongside the intended one. Genetic influence is well documented, and families often report the same finding across generations, which means a parent with supernumerary teeth may see the pattern repeat in a child.
A subset of hyperdontia cases sits within recognised genetic syndromes. These conditions carry dental features alongside skeletal, skin or developmental findings, and the extra teeth sometimes serve as an early clue that prompts broader medical assessment:
- Cleidocranial dysplasia, marked by abnormal development of the skull and collarbones, frequently accompanied by multiple unerupted supernumerary teeth.
- Gardner syndrome, a rare condition combining intestinal polyps with skeletal and dental abnormalities
- Cleft lip and palate, where extra teeth commonly develop near the cleft site
- Fabry disease, an inherited metabolic disorder with wide-ranging effects
- Ehlers-Danlos syndrome, a connective tissue disorder associated with several oral findings
- Trichorhinophalangeal syndrome, producing distinctive facial features alongside hair, nail and tooth abnormalities
- Rubinstein-Taybi syndrome and Nance-Horan syndrome, both of which include dental anomalies among their features
Non-syndromic cases make up the clear majority. Environmental and local factors such as trauma to the developing jaw, infection during tooth formation, and certain medical treatments in early childhood have all been proposed as contributors, though none carries the explanatory weight of the genetic model.
Types of Hyperdontia Supernumerary Teeth
Dentists classify extra teeth along two axes: where they sit and what shape they take. The distinction matters because position predicts the complications likely to follow, while shape often indicates how straightforward removal will be. The table below sets out the categories a patient is most likely to hear during a consultation.
| Classification | Type | Description |
| By position | Mesiodens | The most common supernumerary tooth, sitting between or behind the two upper front teeth |
| By position | Paramolar | An extra tooth alongside the molars, usually toward the cheek side |
| By position | Distomolar | A tooth positioned behind the last molar, sometimes called a fourth molar |
| By shape | Conical | A small peg-shaped tooth found near the front of the mouth |
| By shape | Tuberculate | A barrel-shaped tooth with multiple cusps, often paired and frequently impacted |
| By shape | Supplemental | A near duplicate of a normal tooth, matching its neighbour in form |
| By shape | Compound odontoma | A cluster of small tooth-like structures rather than one defined tooth |
| By shape | Complex odontoma | A disorganised mass of dental tissue without recognisable tooth form |
Mesiodens dominates the statistics and also explains why so many cases surface during childhood orthodontic assessment. A conical mesiodens may erupt and cause little trouble, whereas a tuberculate form tends to remain impacted and block the central incisor behind it.
How Hyperdontia Diagnosis Works
Hyperdontia diagnosis is straightforward once a tooth has erupted, since the extra structure is visible to the patient, a parent, or the dentist at a routine appointment. The more consequential cases are the hidden ones. An impacted supernumerary tooth sits entirely within bone, produces no visible sign, and surfaces only through imaging ordered for an unrelated reason.
Clinical examination comes first, with the dentist counting teeth, checking eruption timing against expected milestones, and noting any crowding or midline shift. Imaging follows. Panoramic and periapical dental X-rays reveal the number, position, and orientation of hidden teeth, and cone beam computed tomography adds a three-dimensional view when a tooth sits close to the nasal cavity, a nerve, or the root of a neighbouring tooth.
Why Hyperdontia Shows So Clearly on Skull Imaging
Images of a hyperdontia skull circulate widely because radiographs and anatomical specimens display what the mouth conceals. Supernumerary teeth lodged high in the maxilla, angled sideways, or stacked behind the incisors become unmistakable once bone is rendered transparent. This visibility carries practical value: an orthodontist planning tooth movement needs to know exactly what lies in the path before applying force, and a surgeon planning removal needs the same information to protect adjacent roots.
Referral to an oral surgeon or orthodontist frequently follows the imaging stage, particularly in growing patients where timing influences the outcome. Early detection in children allows intervention before a permanent tooth is permanently displaced.
Hyperdontia Treatment Options
Hyperdontia treatment is shaped by three variables: the number of extra teeth, their position relative to healthy structures, and the patient’s age. A quiet supernumerary tooth causing no crowding, no eruption delay, and no cleaning difficulty may simply be monitored with periodic radiographs. Where the tooth interferes with function, alignment, or hygiene, active management becomes the better course.
Clinicians generally work through the following options, often in combination:
- Extraction removes the supernumerary tooth and remains the most common intervention, especially for an impacted mesiodens obstructing a permanent incisor
- Orthodontic treatment with braces or clear aligners closes the resulting space and corrects rotation or displacement left behind
- Surgical exposure and traction guides a blocked permanent tooth into position after the obstruction is cleared
- Restorative care addresses damage already sustained by neighbouring teeth, using fillings, crowns or veneers where enamel or roots have been compromised
- Orthognathic or oral surgery is reserved for extensive multiple hyperdontia affecting jaw development
- Active monitoring suits asymptomatic teeth in positions that pose no risk to adjacent roots
Where Braces Fit Into the Plan
Orthodontics rarely resolves hyperdontia on its own, since braces move teeth rather than eliminate them. The sequence usually runs in the opposite order: the extra tooth is removed, then appliances close gaps, derotate displaced teeth, and restore the midline. In a small number of cases where a supplemental tooth closely resembles its neighbour and the arch has room, an orthodontist may retain the extra tooth and align it within the row.
The Cost of Leaving Extra Teeth Alone
Untreated crowding complicates everyday hygiene, and plaque that cannot be reached reliably progresses to decay and gum inflammation. Overlapping surfaces trap debris, which raises the risk of cavities and periodontal problems over time. Impacted supernumerary teeth carry their own risks, including resorption of neighbouring roots and, less commonly, cyst formation in the surrounding bone. Dental visits twice a year give a clinician the opportunity to identify these changes while they remain reversible.
Living Confidently With Hyperdontia
Hyperdontia occupies an unusual place in dentistry: common enough to appear in general practice regularly, yet variable enough that no two treatment plans look identical. The deciding factor is rarely the extra tooth itself but what it does to everything around it. A conical tooth sitting quietly in bone may never require intervention, while a tuberculate mesiodens blocking an incisor calls for prompt action. Accurate imaging, timing matched to dental development, and a plan that pairs removal with alignment produce outcomes that patients find difficult to distinguish from a mouth that never had hyperdontia at all. Treatments for hyperdontia are available at Smile Team, and our clinical team welcomes enquiries about assessment and planning. For additional information about hyperdontia and how to fix it, you can contact us.
Frequently Asked Questions About Hyperdontia
Can hyperdontia be cured?
Hyperdontia cannot be prevented or reversed, because the extra tooth bud forms during development long before any treatment is possible. The condition is, however, fully manageable. Removing the supernumerary tooth and correcting its effects on alignment resolves the clinical consequences permanently, since another extra tooth will not develop in its place.
Can braces fix hyperdontia on their own?
Braces correct the crowding, rotation, and spacing that hyperdontia produces, yet they cannot eliminate a tooth. Most treatment plans combine extraction with orthodontics, with the sequence decided by the position of the extra tooth and the stage of a patient’s dental development.
Is hyperdontia dangerous?
Hyperdontia is not life-threatening and carries no systemic risk in isolation. The concern lies with the secondary effects: blocked eruption, displaced roots, difficulty cleaning, and occasional cyst formation around an impacted tooth. Multiple supernumerary teeth warrant closer attention, as that pattern sometimes signals an underlying syndrome worth investigating.
At what age is hyperdontia usually detected?
Detection clusters between ages 5 and 12, when permanent teeth begin erupting, and any delay or asymmetry becomes apparent during routine checkups. Cases involving fully impacted teeth frequently go unnoticed into adulthood and emerge only when radiographs are taken for wisdom teeth, implants, or orthodontic planning.
Does removing a supernumerary tooth hurt, and how long is recovery?
Extraction is performed under local anaesthesia, so the procedure itself is not painful, with sedation available for deeply impacted teeth or anxious patients. Soft tissue healing typically takes one to two weeks. In children, a blocked permanent tooth may need several months to a few years to erupt into its corrected position after the obstruction is cleared.
You can read our previous article at https://smileteamturkey.com/blog/laminate-veneers-vs-porcelain-veneers/